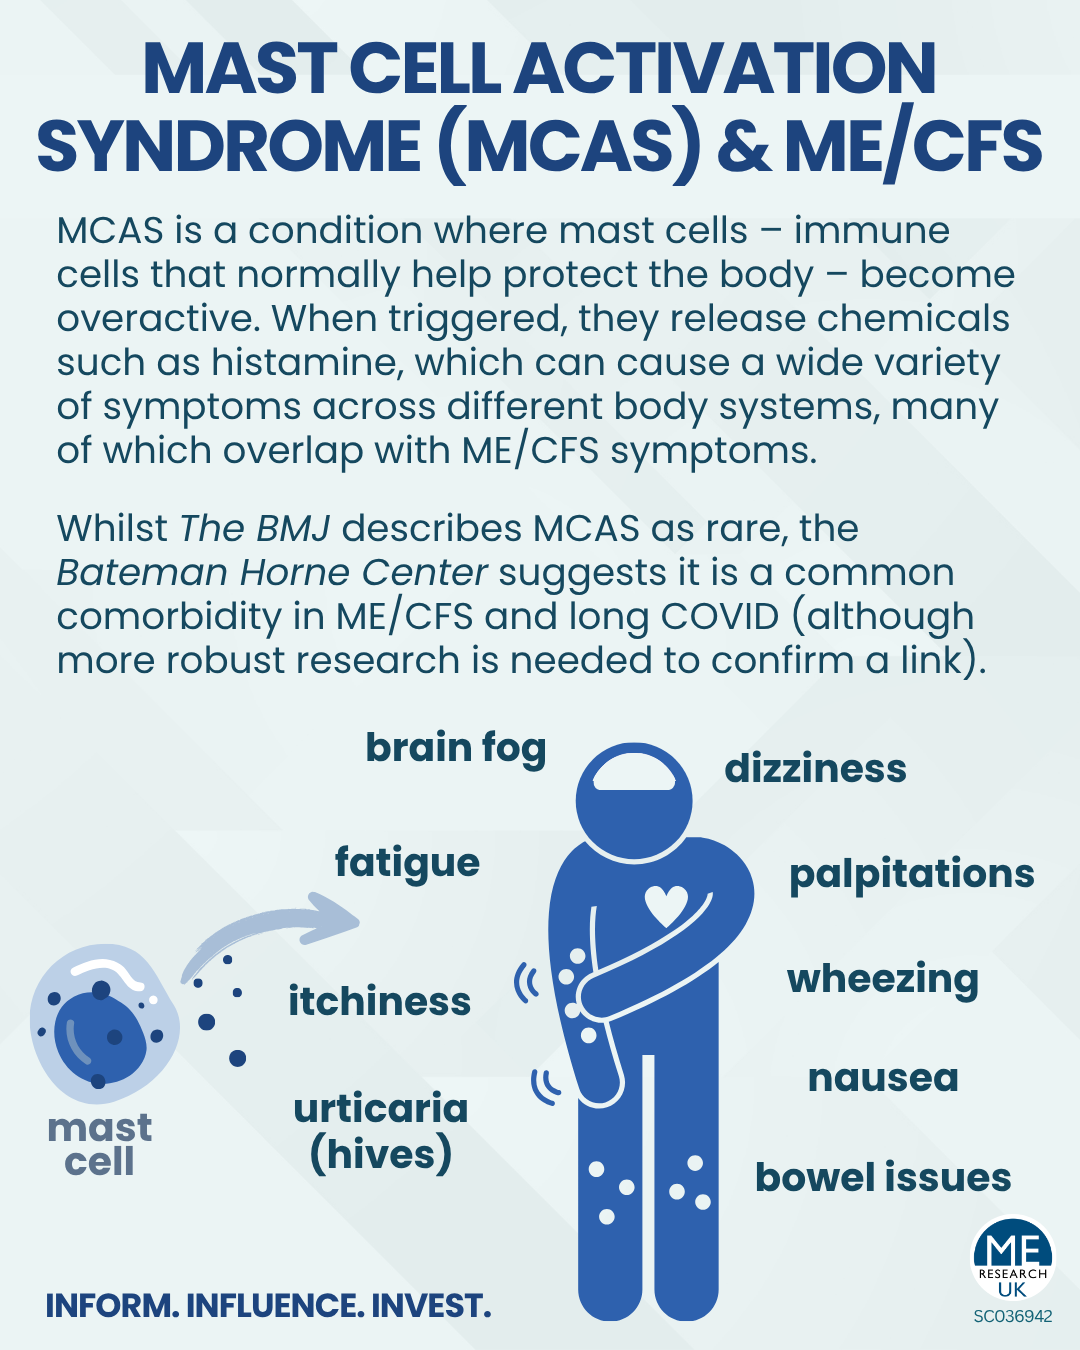
Mast cell activation syndrome (MCAS) is a condition where mast cells – immune cells that normally help protect the body – become overactive. When triggered, they release chemicals such as histamine, which can affect multiple body systems, causing a wide variety of symptoms (such as hives) that can overlap with ME/CFS symptoms. It is thought this activation of mast cells can contribute towards symptoms of dysautonomia (dysfunction of the autonomic nervous system).
Whilst BMJ Best Practice describes MCAS as rare, the Bateman Horne Center suggests it is a common comorbidity in ME/CFS and long COVID . It is possible that MCAS is underdiagnosed, since its symptoms are broad and often mistaken for other conditions. However it is important to mention that diagnosing MCAS is complex.
Interest in the condition is surging: a Medscape article notes that specialist referrals have risen substantially over the past 15 years. Some experts attribute this trend to greater disease awareness, and increased access to online information (and misinformation). One expert – Dr Theoharis Theoharides – pointed to COVID as “a potential contributor to the condition”.
Symptoms and common triggers
MCAS can affect many parts of the body. Common symptoms include:
- Skin: flushing, urticaria (hives), itching
- Heart and circulation: palpitations, chest pain
- Lungs: coughing, wheezing
- Gut: nausea, vomiting, diarrhoea, constipation, throat tightness, difficulty swallowing
- General / brain-related: fatigue, dizziness, brain fog, lightheadedness
- Severe: in some cases, anaphylaxis (a serious allergic-type reaction)
Identifiable triggers vary widely between individuals, but commonly include infections, temperature changes, high-histamine foods, alcohol, certain medications (such as NSAIDs), sunlight, stress, and exercise.
Diagnosis and expert debate
MCAS can be difficult to diagnose because the symptoms overlap with other conditions. Clinicians may additionally look for a rise in mast cell markers (such as serum tryptase) during acute episodes and symptom improvement from mast cell-targeting medications.
However, there is debate amongst specialists regarding how MCAS should be diagnosed. Whilst certain experts advocate for strict criteria requiring objective lab evidence of specific mediators like serum tryptase, other experts argue that current tests fail to capture the complexity of MCAS and leave many symptomatic patients without answers.
What does the research say?
Research directly linking MCAS and ME/CFS is still sparse, but various studies offer important insights:
- A 2025 study analysing two cohorts – consisting of a 687-patient survey dataset and a retrospective clinical group of 383 ME/CFS patients – found that mast cell activation (MCA) “appears to be a frequent and clinically relevant comorbidity in ME/CFS and is associated with a higher prevalence of [orthostatic intolerance], particularly POTS.” However, it should be noted that there was a distinct lack of objective lab testing, which was only conducted in 12 ME/CFS patients (3.1% of the cohort), meaning that no statistical analysis could be performed on this parameter.
- An prior review by a different research team noted that whilst a direct association between MCAS and ME/CFS appears infrequent, “there is clear evidence for a role of histamine and allergic predisposition in ME/CFS and long COVID. The most convincing evidence for the involvement of histamine is the alleviating action of long-term symptoms of post-COVID-19 infection upon the anti-histamine treatment.” As we know, for a proportion of individuals with long COVID, the COVID-19 virus triggered ME/CFS.
The researchers also proposed linked mechanisms between MCAS, ME/CFS, postural orthostatic tachycardia syndrome (PoTS), decreased cerebral blood flow, and small fiber neuropathy (SFN). They suggest that all of these may involve over-release of inflammatory and vasoactive (affecting blood vessel diameter) molecules/substances and dysfunction of certain cell receptors (β2-adrenergic receptors). - Another study suggested that COVID-19 infection might worsen existing undiagnosed MCAS, possibly explaining why some individuals with long COVID experience symptoms that could suggest MCAS.
Management
Treatment usually focuses on:
- Avoiding known triggers e.g. minimising stress, following a low-histamine diet
- Medications such as antihistamines (H1 and H2 blockers), leukotriene receptor antagonists, and mast cell stabilisers
Emergency treatment with adrenaline (epinephrine) is needed for severe reactions such as anaphylaxis.
Conclusion
Whilst MCAS and ME/CFS are not the same condition, there is an overlap in symptoms and potentially in biological pathways. For individuals with ME/CFS who suspect co-occurring MCAS, it may be worth exploring with a healthcare provider, as treatment for MCAS may reduce the overall burden of symptoms.
This article is provided as part of Dysautonomia Awareness Month – with MCAS falling under that broad umbrella – and is not intended as a full exploration of MCAS or its relationship with ME/CFS. Research exploring MCAS in relation to ME/CFS is limited/sparse.